The library
Stacks,
explained.
Combining peptides is standard practice in clinics and almost entirely untested in trials. Here is the difference.
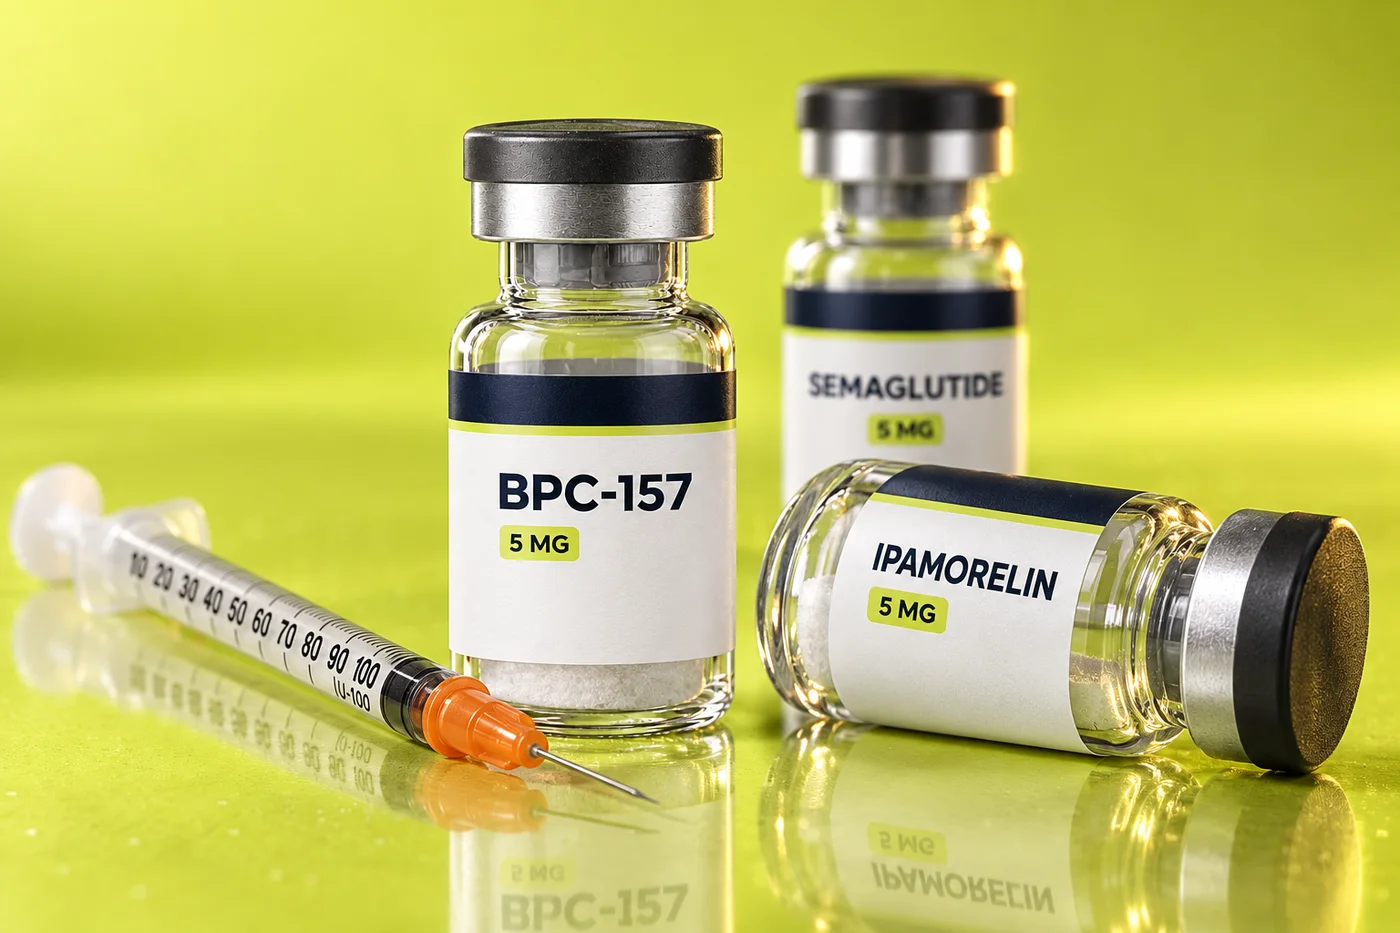
What stacking means
A stack is simply two or more peptides used in the same protocol, usually chosen because they are described as working through different mechanisms toward the same goal. One compound is said to raise a hormone signal, the second to amplify the pulse. One is said to improve local blood supply, the second to bring repair cells to the site. The word sounds technical, and underneath it is an ordinary idea from pharmacology: two drugs with separate mechanisms can do more together than either alone.
Why clinics combine
The reasoning is real, not invented for marketing. Growth hormone release, for example, is controlled by two separate systems, so a GHRH analog and a ghrelin receptor agonist push the same pulse through different doors, and hormone studies of each compound alone support the mechanism. Combining also lets a clinic use smaller amounts of each compound instead of pushing one toward the top of its range, which is a sound principle everywhere else in medicine.
Then there is the commercial reason, and it deserves saying. A stack is two products instead of one, sold as a program rather than a vial, which is why almost every clinic menu is organized around combinations.
The part nobody proves
For the popular peptide stacks, no completed human trial has studied the combination. Not the growth hormone pair, not the healing pair, not the gut protocols. The evidence that exists covers single compounds, and in most cases it is hormone measurements in volunteers or healing outcomes in rodents rather than results a patient would feel.
That has three consequences worth holding onto. The combined dose response is unknown, so nobody can say whether two half doses work like one full dose or like something else. Interactions are unmeasured, because measuring them requires the study that was never run. And attribution breaks down: when two new compounds start on the same day and something changes, good or bad, there is no way to know which one did it.
Rules that keep a stack sane
None of these rules comes from a trial of a combination, because those trials do not exist. They come from how medicine handles two unknowns at once.
- Add one new compound at a time, never two on the same day
- Have a licensed physician review the whole protocol before it starts
- Start every compound at the lowest dose in its range
- Give each addition a few weeks before judging what it did
- Stop everything at once if side effects appear, then restart one at a time
- Keep bloodwork and a written log so the record is not memory
Questions people ask
Is stacking peptides safe?
What peptides should not be combined?
How many peptides can you stack at once?
Do peptide stacks need to be cycled?
Sources: FDA — bulk substances safety list · FDA — dietary supplement ingredient directory · PubMed — growth hormone secretagogue research · WADA Prohibited List